
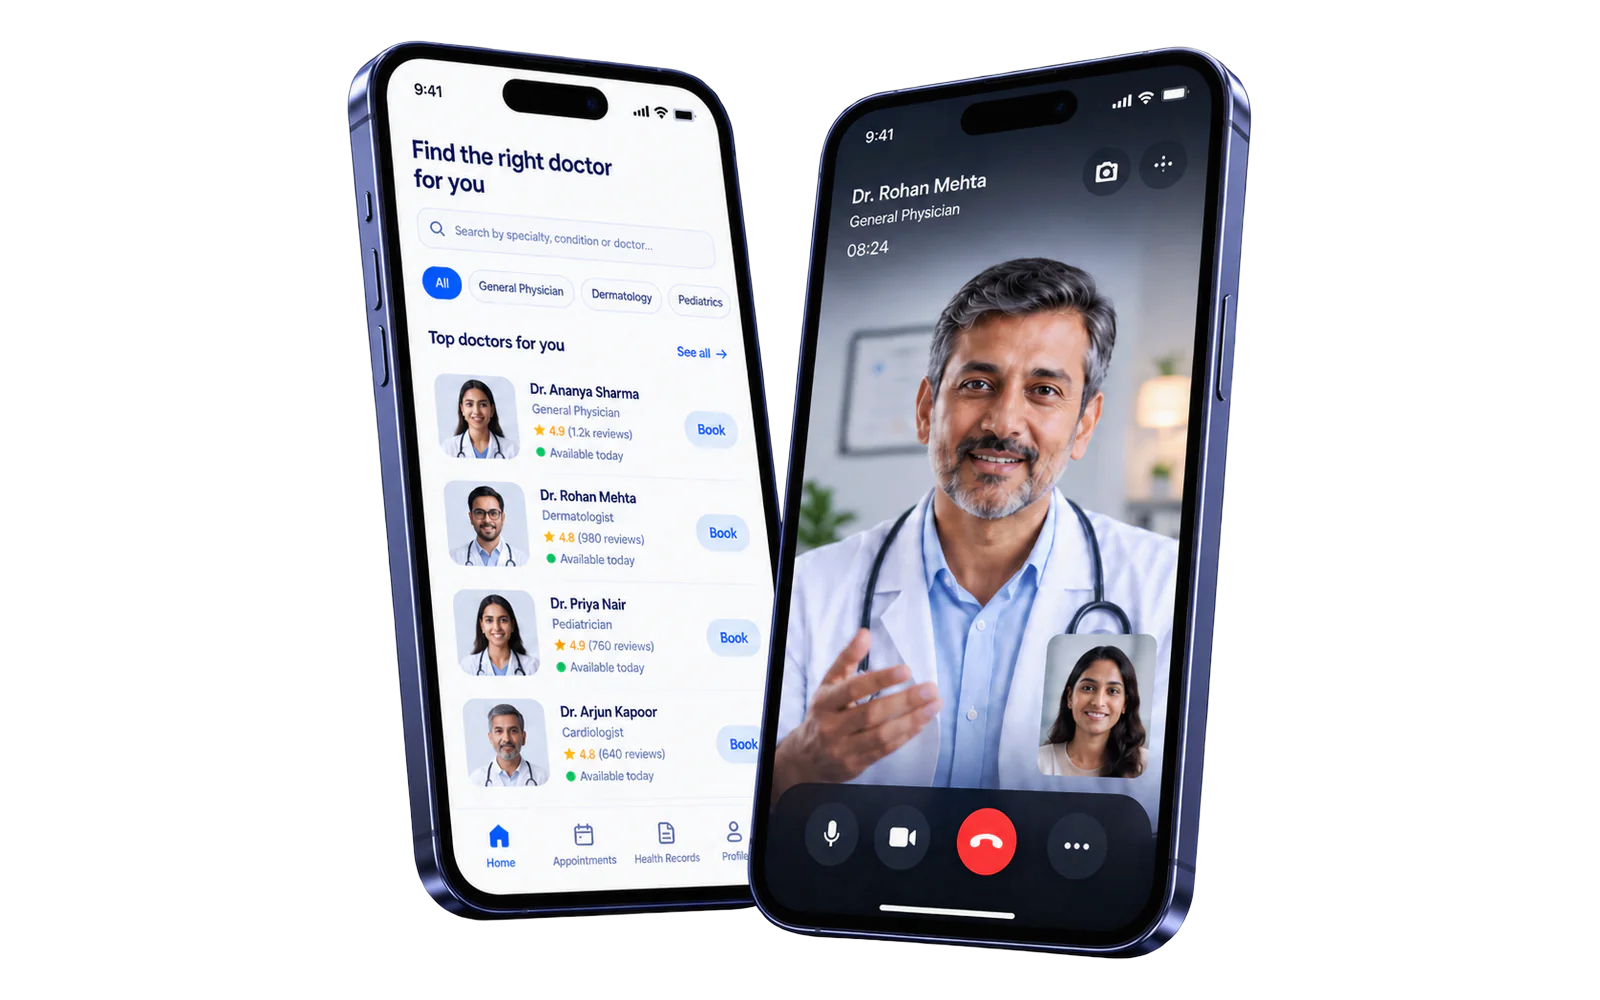
Who, why, and what
Teleconsultation gives people healthcare access through virtual doctor visits, removing the in-person appointment for everything that doesn't need one. Its value is three things: convenience, timely access, and reach into places a clinic doesn't cover.
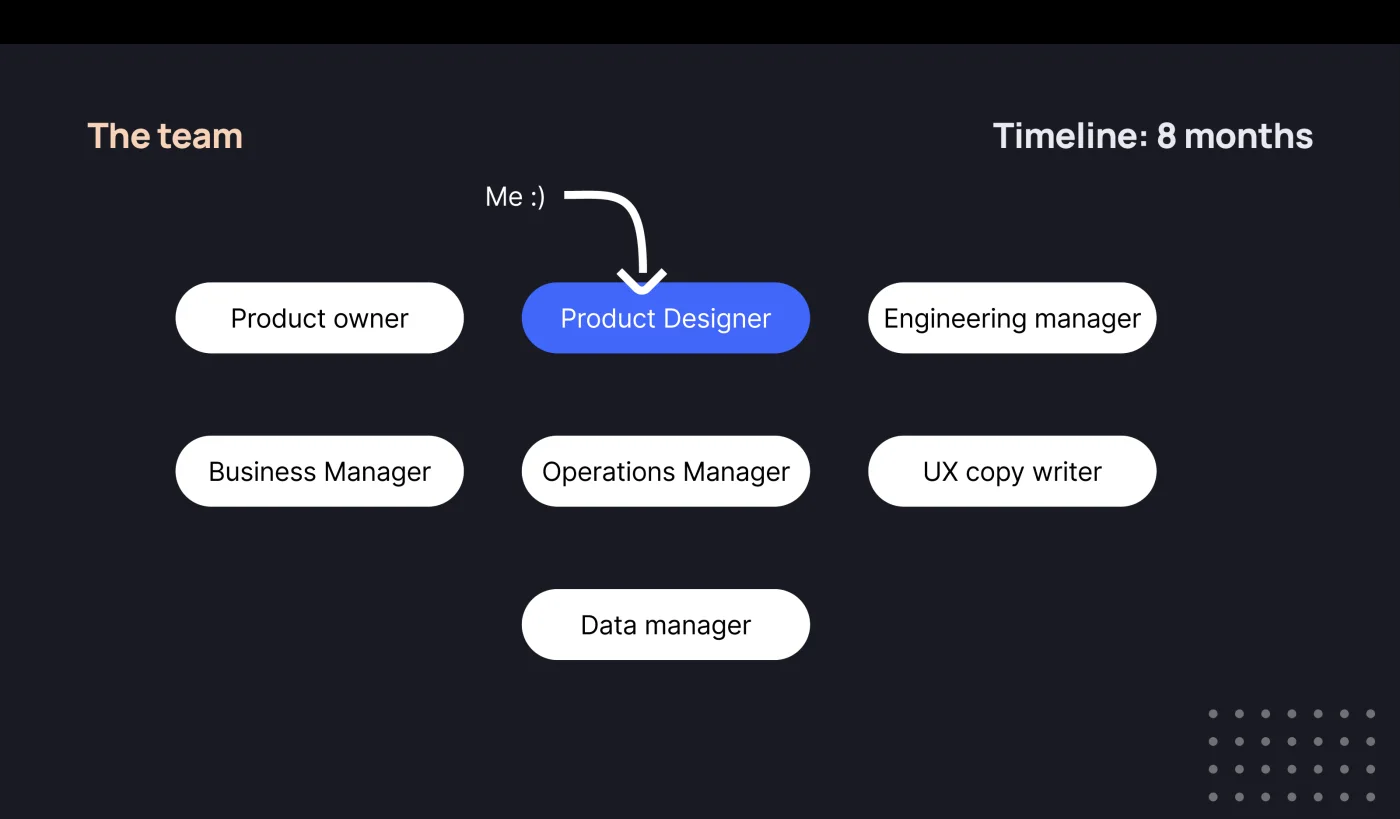
I was the product designer on an eight-month build, alongside a product owner, an engineering manager, business and operations managers, a data manager and a UX copywriter.
The product sits inside corporate health plans — so the user is an employee with a working day to protect, not a patient with an afternoon free.
The business problem
The pandemic significantly increased demand for teleconsultation inside corporate healthcare plans. Existing solutions struggled — for employees and for the medical professionals on the other end.
- Scheduling inefficiencies
- Engagement and communication issues
- Data security concerns
“As a result of these challenges, corporations struggle to offer a seamless and efficient teleconsultation experience for their employees.”

What the market already knew
Research ran on two tracks — patients and doctors. This case study covers the patient side.
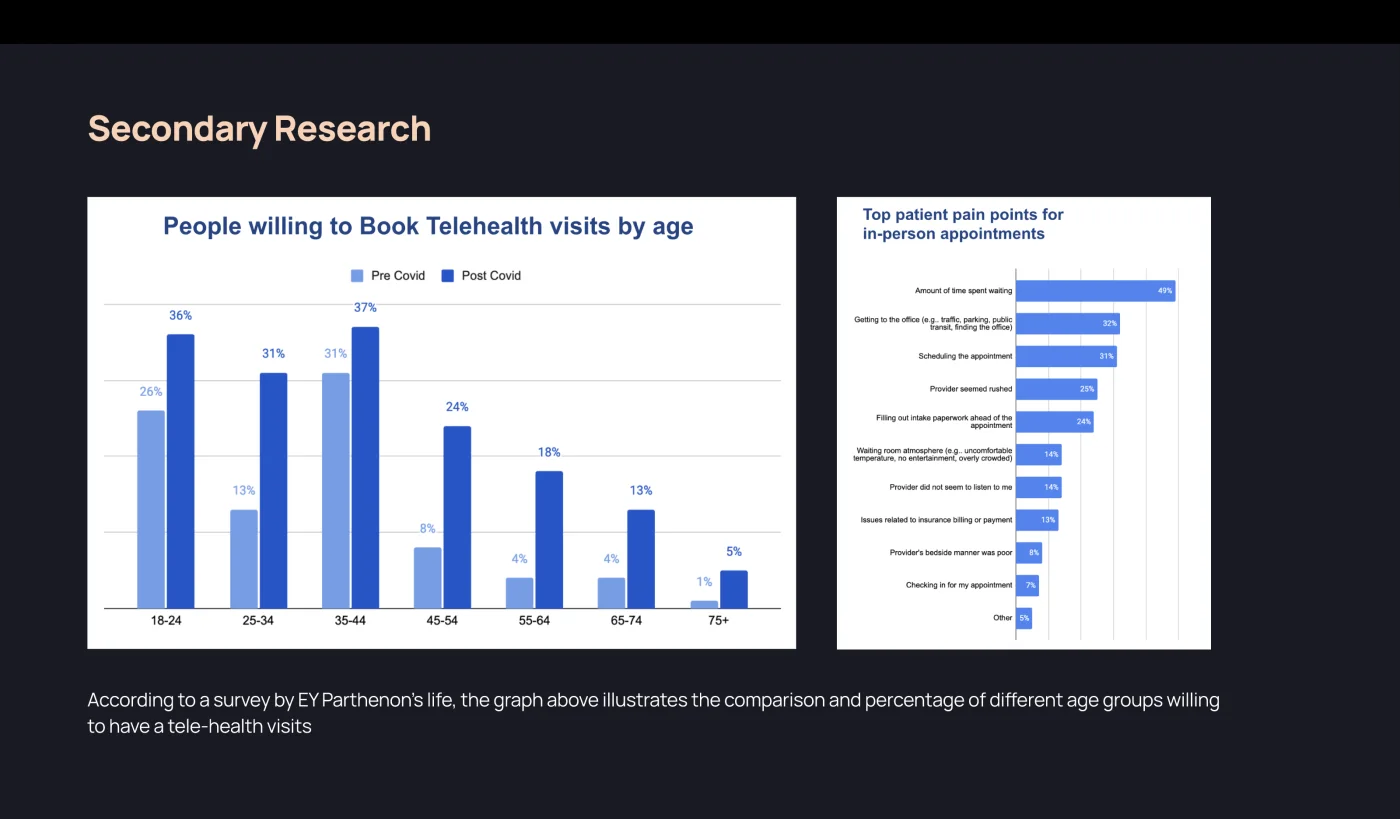
Willingness to book a telehealth visit rose in every age band after Covid — and rose most among the people least likely to have tried it before. Among 25–34s it went from 13% to 31%; among 45–54s from 9% to 24%. The demand was not a young-professional phenomenon.
What competitors got right and wrong
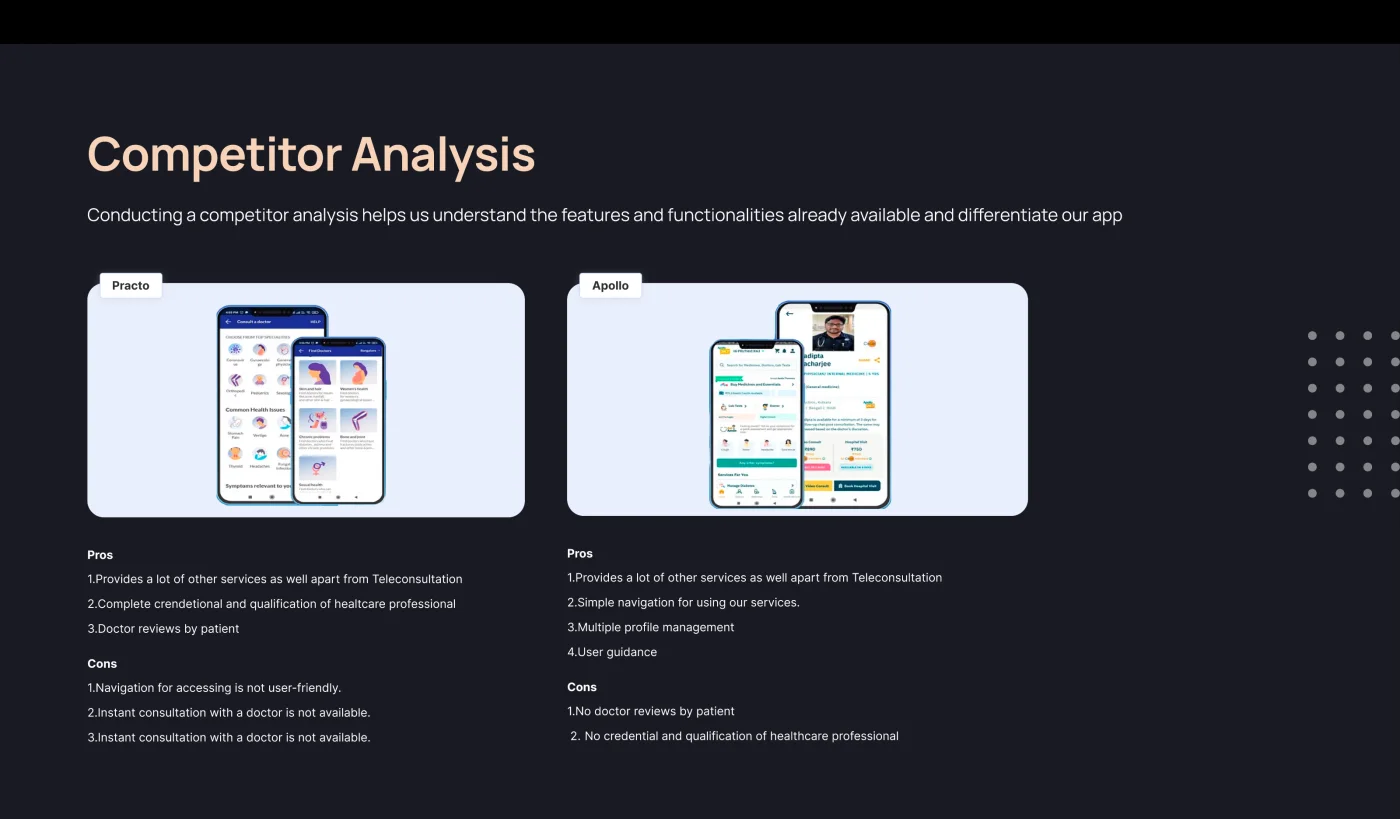
Practo and Apollo both bundled teleconsultation into a wider services app. Both had the same gap.
Practo had credentials and qualifications for every healthcare professional and doctor reviews from patients — but navigation to reach them was not user-friendly, and instant consultation was not available.
Apollo had simpler navigation, multiple profile management and user guidance — but no doctor reviews and no credentials.
Neither offered an instant route to a doctor. That absence became the thing to design for.
Who I studied
Twenty interviews with the people corporate plans actually cover.
| Total | 20 interviews |
| Age group | 25–45 years |
| Gender | 13 male, 7 female |
| Occupation | Corporate employees · busy professionals · home makers |
| Screened on | Technical knowledge · availability of a smartphone |

What patients said
Two numbers set the design constraints, and one finding exposed a hole in the product nobody had named.
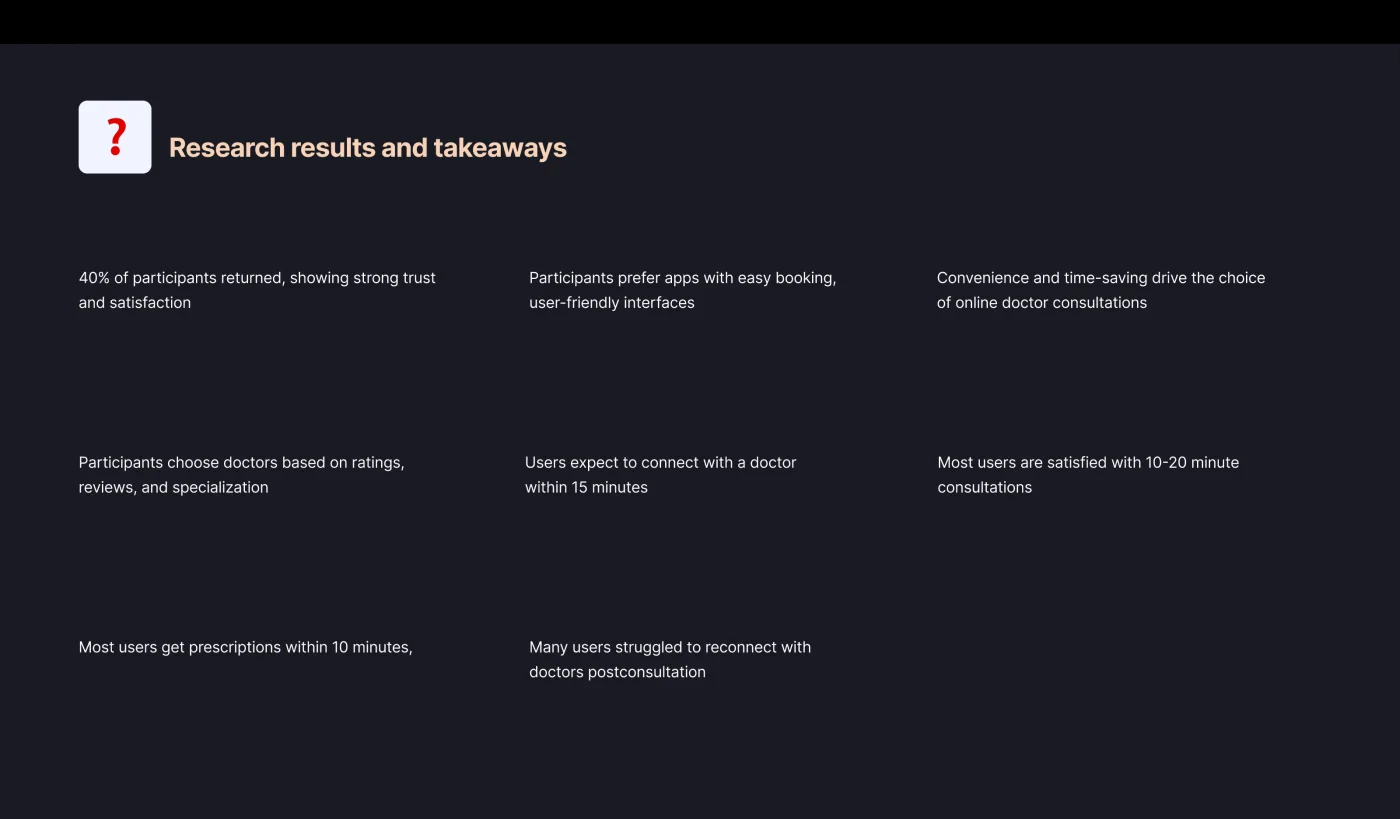
Convenience and time-saving drive the choice of an online consultation over an in-person one — not cost, and not clinical preference.
Trust is delegated to signals. Participants chose doctors on ratings, reviews and specialisation. That is why the competitor gap mattered: an app without credentials is asking for trust it has given the user no way to grant.
Many users struggled to reconnect with doctors after the consultation.
This was the finding that changed the scope. The journey was being designed up to the consultation, and the need continued past it — a prescription question, a symptom that changed, a follow-up nobody had a route to.
The core problem
“Busy schedules and limited in-person access leave me constantly worried about my health, yearning for a convenient way to connect with a trusted doctor virtually.”

Two approaches, and why the first one failed
Pen and paper first — the fastest way to portray early ideas and eliminate the ones not addressing the problem. I started from patterns users already knew, to reduce the learning curve.
Approach 1 — the booking form
A form-based approach for booking a teleconsultation. It worked, and I rejected it:
- Users are required to provide additional input within this approach.
- It may increase the cognitive load on users when booking consultations with doctors.
Asking a worried person to fill in a form is the wrong first move.
Approach 2 — the circular architecture
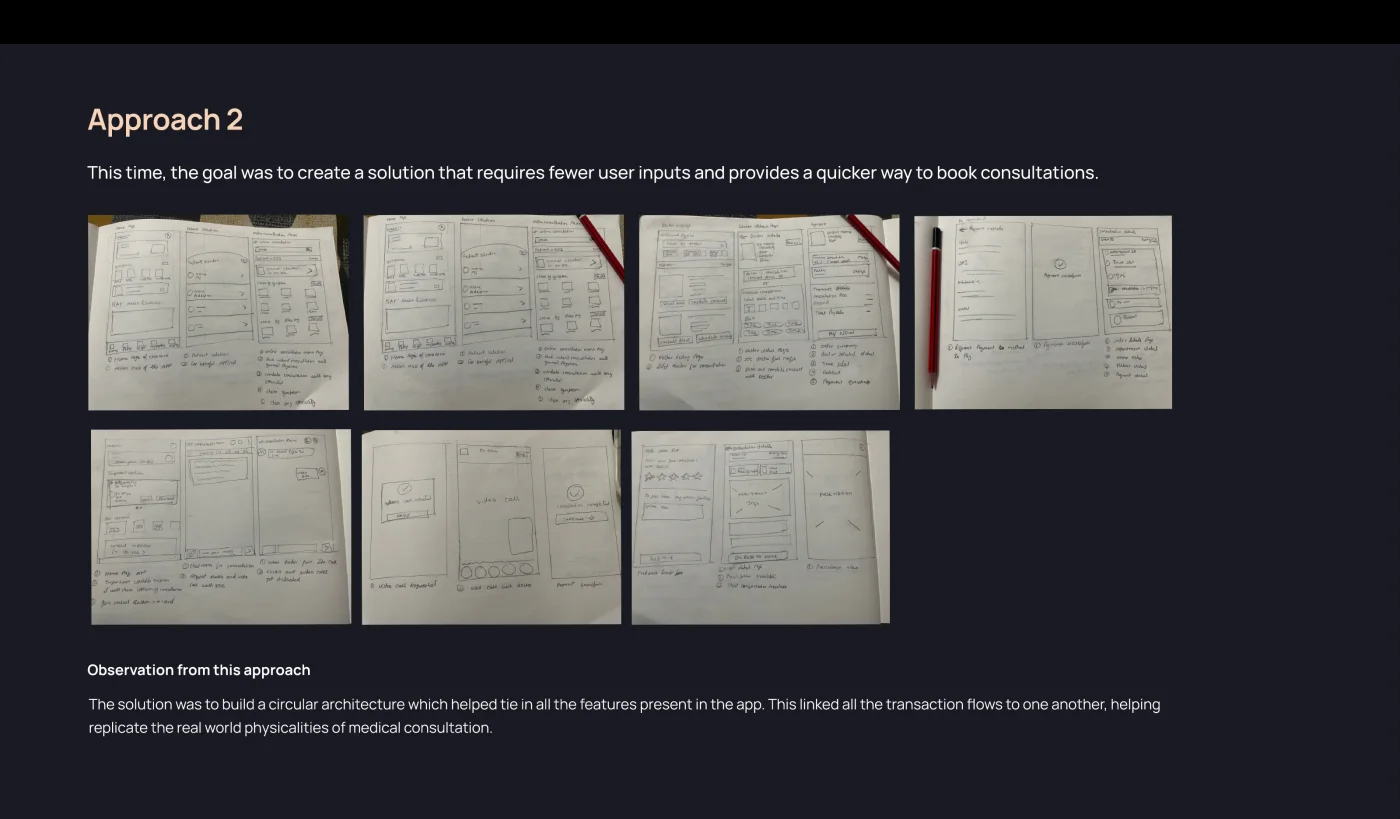
The goal this time was fewer user inputs and a quicker way to book.
The solution was a circular architecture that tied together every feature in the app, linking all transaction flows to one another — replicating the real-world physicality of a medical consultation rather than modelling it as a checkout.

The scheduling journey, in greyscale
Nine steps from home screen to a paid, confirmed consultation: patient selection, online consultation, doctor listing, doctor details, order summary, payment, confirmation, and the order detail afterwards.

Usability testing
An unmoderated test of the teleconsultation journey. It produced the feature that defines the product.

Two recommendations came out
Introduce an “Instant Consultation” option that lets users connect with a doctor when they need immediate assistance — the gap neither Practo nor Apollo had filled.
Improve the clarity and usability of the specialty selection process. Choosing a specialisation is where a worried person is least equipped to decide, and where the old flow asked the most of them.
“Sometimes you just can't wait — having an instant connection option for emergencies would be a game-changer.”
Participant quote from the study.
The shipped journey
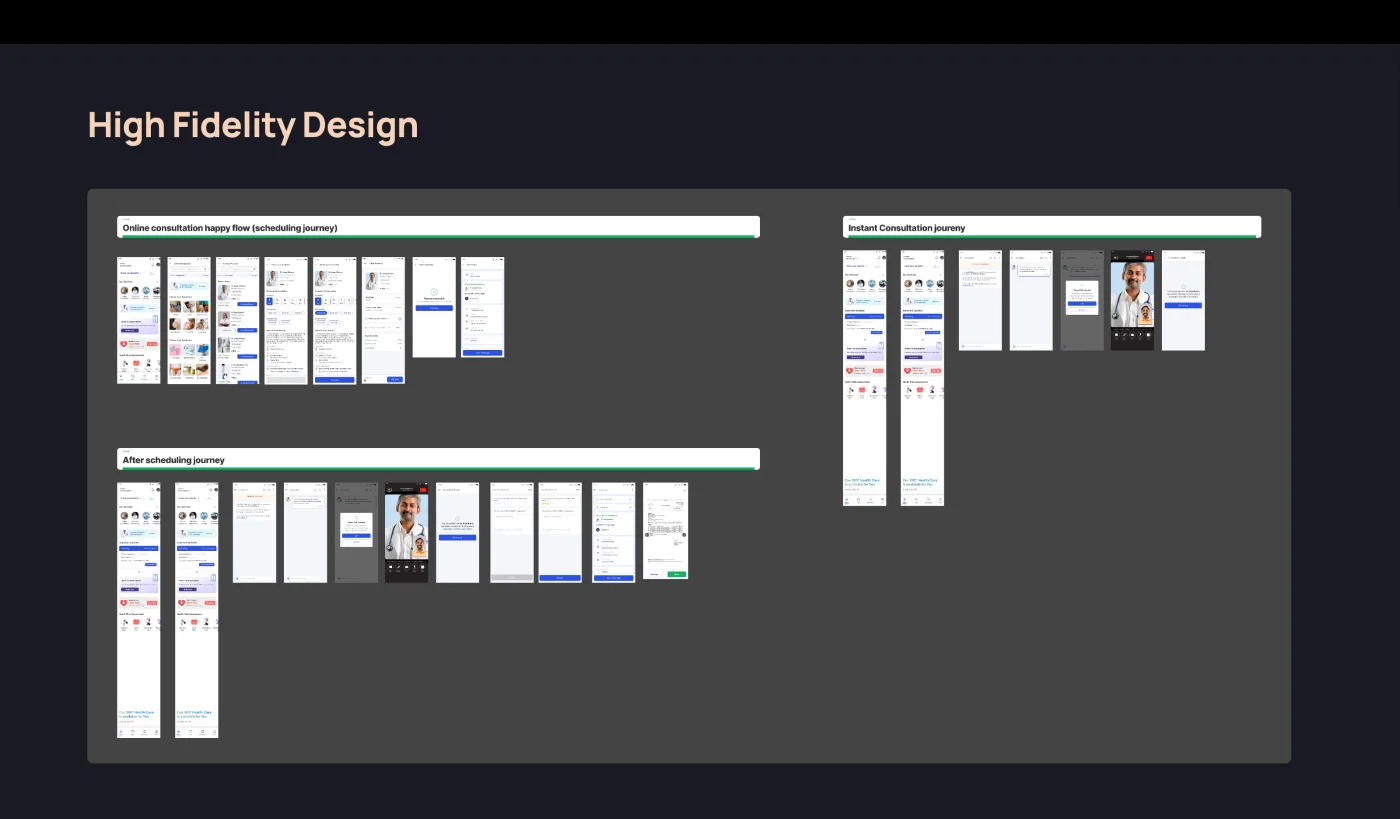
Three flows, built from one architecture: the scheduled consultation, the instant consultation, and everything that happens after the call ends — the part the research said was missing.
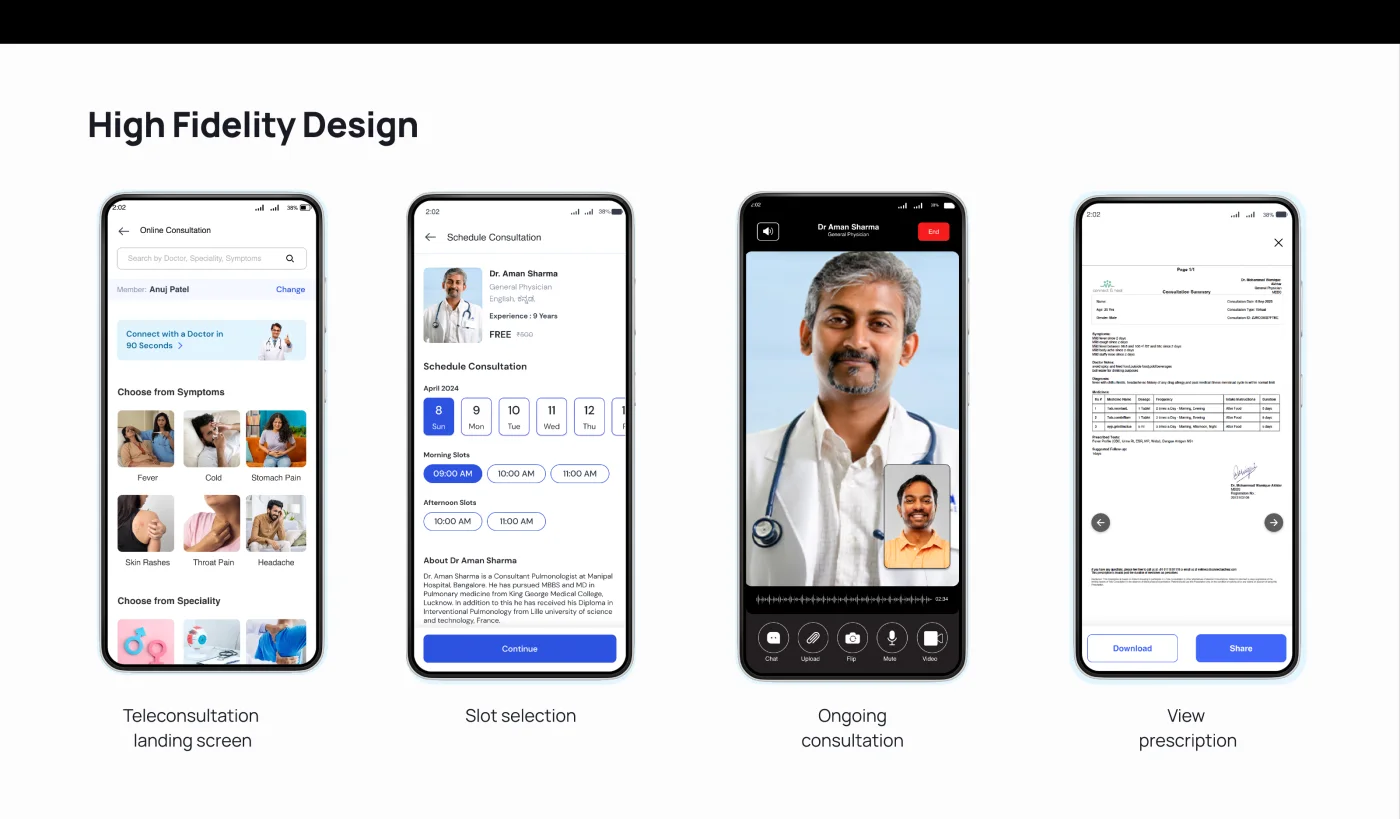
“Connect with a Doctor in 90 seconds” sits at the top of the landing screen, above symptom and specialty selection. The instant route is the default offer; scheduling is the alternative, not the other way round.
Symptoms come before specialities. A user who knows they have a sore throat does not necessarily know they need an ENT. Leading with symptoms removes the decision the testing showed people struggled with.
The prescription is a destination, not an email. It can be viewed, downloaded and shared from inside the app — which is also the answer to people struggling to reconnect after a consultation.
Doctor credentials are on the booking screen — qualification, experience, hospital — because the research said trust is delegated to exactly those signals.
Results and what I learned
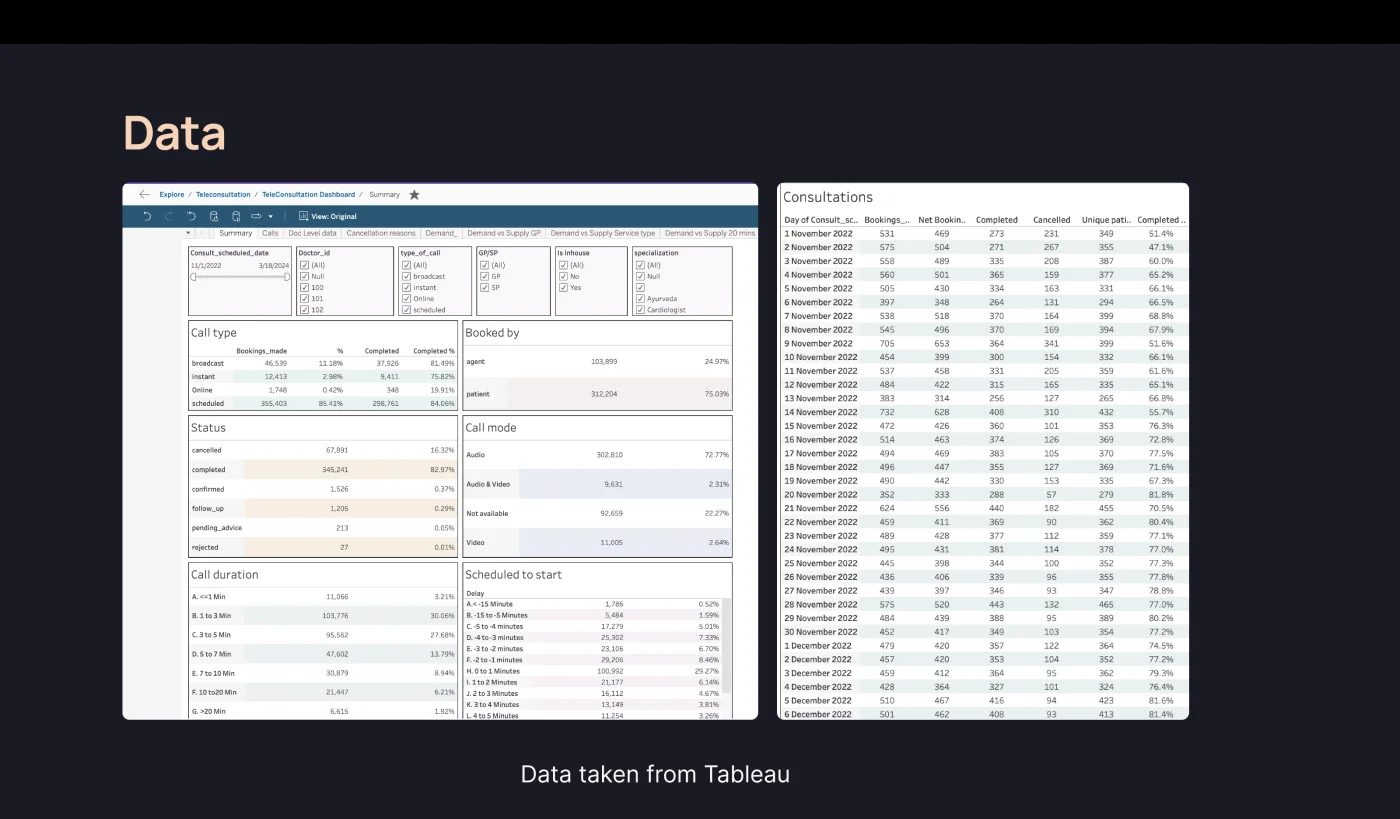
Volume peaked in the Covid year and settled afterwards, as in-person care reopened. The number worth reading is the floor, not the peak: teleconsultation held above 400,000 consults a year once it was competing with a clinic visit again rather than substituting for one.
What I would carry to the next one
- Human-centred design. Insights from a varied group of users produced a more usable product than designing for the average would have.
- Early engineering involvement. Prevented technical issues and made development smoother.
- A strong foundation. Focusing first on core functionality saved time and resources later.
- Design systems. Kept consistency and efficiency across teams.
- Leadership support. Won by demonstrating potential ROI, which made early buy-in possible.